3 Common Drugs You May Not Need

In this article I warn about commonly used medications that offer limited benefits while posing significant risks, especially for older adults. Patients should regularly review medications with healthcare professionals and avoid stopping drugs abruptly.

I’m sharing an article I found at KFF Health News. It caught my attention because I’ve written a similar article about overused drugs.

We applaud the introduction of new drugs that can save a life or treat an untreated chronic condition. But many drugs are used inappropriately, either because they are ineffective for that purpose or unnecessary for anything.

This article focuses on drugs used in older adults, but the issue is not unique to that age group. The point is to only use drugs when there is a reason to do so, when you and your doctor identify a specific goal to achieve. Otherwise, you may waste your money and possibly endanger your health.

3 Common Drugs Older Adults Might Be Overusing

The scenario often unfolds like this: Medical researchers investigate a frequently used drug and report that it’s less effective for older patients than previously thought, or that its risks outweigh its benefits in older adults. More studies follow, confirming those findings.

After a few years, medical associations revise their guidelines, warning that the drug in question should be avoided or at least prescribed more selectively. It might be added to the Beers Criteria, an influential list of potentially inappropriate medications for older patients, published by the American Geriatrics Society.

If the drug’s role is preventive, the U.S. Preventive Services Task Force, an independent expert panel, may weigh in with cautions. The FDA may issue “black box” warnings about concerning side effects.

After a few more years, researchers look at broad national data to see whether use of this drug declined. Often, the answer is: Yes, but not enough. Sometimes, though, use didn’t decline much at all or actually increased.

“Medications are like barnacles, They’re easy to start, but they can be hard to stop.”

said Michael Steinman, a geriatrician at the University of California-San Francisco and co-director of the U.S. Deprescribing Research Network.

This medical inertia partly reflects the time lag involved in disseminating findings. “Clinicians have a million things they need to know and attend to, and information may take a while to get to them,” Steinman said.

But it also reflects the way “clinicians and patients get used to treating conditions in certain ways,” he said. “They become ingrained habits.” Finding alternative approaches is challenging, so “it’s easy to go with what you know.”

Recent studies of three medications or classes of drugs widely used among older Americans illustrate the problem.

The Drawbacks of Benzodiazepines

Scientists began raising alarms about benzodiazepines more than 20 years ago. Prescribed for insomnia and anxiety, “they offer prompt relief,” said Mark Olfson, a psychiatrist and epidemiologist at Columbia University.

The problem? Benzodiazepines (including Valium, Xanax, and Ativan) and the related “Z” drugs (Ambien, Lunesta) “may impair balance, coordination, and cognition that can translate into falls and fractures and motor vehicle accidents,” Olfson said. In patients also taking opioids for pain, benzodiazepines can cause overdoses.

Moreover, “once you’ve taken them for a period of time, you develop a dependence,” Olfson added. “When you come off them, you may develop withdrawal symptoms.”

So what’s happened to benzo use among older adults, who are more sensitive to these effects? In a recent examination of prescribing trends, published in the Annals of Internal Medicine, Olfson and his team reported progress. Among people 65 and older, the rate of patients filling prescriptions for benzos dropped to 11.5% in 2024, from about 14% in 2015.

But that decline has stalled since 2020, perhaps related to the COVID-19 pandemic. Moreover, prescribed use actually rose among those over 75, from 12% in 2020 to about 13% four years later.

Dispensing through pharmacies in long-term care facilities more than doubled. And about a third of users were taking the drug for longer than six months, increasing the likelihood of dependence. “It’s worrisome,” Olfson said.

But he cautioned that patients shouldn’t stop benzodiazepines suddenly or on their own, which can provoke withdrawal. “It requires supervised tapering” with a medical professional, he said. “It takes many weeks.”

When Antibiotics May Not Help

For years, the standard treatment for diverticulitis, the inflammation or infection of small pouches that form in the colon, was antibiotics, primarily fluoroquinolones (like Cipro and Levaquin) or amoxicillin-clavulanate (Augmentin).

“It was unquestioned,” said Jesse Sutton, a pharmacist and researcher at the Minneapolis Veterans Affairs healthcare system. “Antibiotics are safe and effective, great, lifesaving drugs, so the mindset was: When in doubt, use them.”

But in 2015, the American Gastroenterological Association recommended against routinely prescribing antibiotics for “uncomplicated” diverticulitis, which represents a great majority of cases. Other medical groups followed suit.

Clinical trials had shown that, for this condition, antibiotics had little or no effect on mortality, the need for surgery, complications, or recurrences. “They hadn’t improved anything,” Sutton said.

And as with any drug, “there are downsides, unintended consequences,” he said. “Side effects from antibiotics account for a substantial amount of emergency room visits” for symptoms like nausea, vomiting, and diarrhea. Antibiotics heighten the risk of the virulent C. difficile infection, too.

Plus, “the more you use antibiotics, the less they work in the future,” Sutton said. The World Health Organization has deemed antimicrobial resistance “a major global health threat.”

So Sutton and his colleagues, studying treatment in 70,000 visits to 120 VA facilities, expected to see antibiotic use for uncomplicated diverticulitis decline over 10 years.

Instead, they reported recently in the Annals of Internal Medicine that antibiotic prescriptions remained nearly universal at 97% of visits, guidelines or no guidelines. The patients would most likely have done as well with a few days of Tylenol and a clear liquid diet.

Antibiotic overuse remains common for other conditions of later life, too, including the kind of urinary tract infections that cause no troublesome symptoms and upper respiratory infections that are typically viral, not bacterial.

In such cases, when a doctor prescribes an antibiotic, “I’d encourage patients to say, ‘Please explain the rationale for doing this,’” Sutton said. “If they don’t, it’s OK to press pause.”

When Aspirin Isn’t the Answer

Aspirin is different. Because it’s cheap and sold over the counter, anybody can start taking it on their own — and millions of older Americans do, thinking it will help prevent cardiac problems.

For people who’ve already had a heart attack, stroke, or cardiac intervention like a stent or bypass surgery, daily low-dose aspirin for “secondary prevention” does lower the odds of another event, studies have demonstrated.

But for “primary prevention” in people who haven’t had one, the guidelines changed in 2019, when the American College of Cardiology and the American Heart Association recommended against aspirin for this purpose in those 70 or older. The U.S. Preventive Services Task Force went further, warning against aspirin for primary prevention starting at age 60.

Large clinical trials had shown scant benefit for aspirin as a primary prevention measure, but there were harms, notably gastrointestinal bleeding. “As we age, the risks of bleeding go up,” said Timothy Anderson, an internist at the University of Pittsburgh who co-directs its Prescribing Wisely Lab. More rarely, but more seriously, aspirin can cause bleeding in the brain.

In a JAMA study published last year, Anderson and his co-author found the message was getting through: Aspirin use for primary prevention, as reported in the National Health and Nutrition Examination Survey, had dropped substantially from 2011 to 2023. But more than a third of those 70 or older were still taking it.

Some caveats: A subgroup of older adults with high risk factors for cardiovascular disease may benefit from aspirin for primary prevention. And, confusingly, some evidence suggests that older patients already taking aspirin face a higher risk of cardiovascular disease if they discontinue it.

“Step 1 is a conversation with your primary care physician” about aspirin, Anderson said. “‘Is this still right for me as I get older?’”

Older patients taking aspirin, many without any medical guidance, “are interested in reducing their risk of heart attack and stroke,” he said. “They’re trying to be proactive and healthy.” But with blood pressure medications and statins for cholesterol, “we have better strategies than aspirin for that.”

The New Old Age is produced through a partnership with The New York Times.

KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.

This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.

Review prevention of heart disease here.

7 Steps to a Healthy Heart

Read about my 7 overused drugs here.

7 Overused Medications

Fear vs. Focus

We shouldn’t fear using medication; instead, focus on using it wisely. After reading this article, what questions do you have about the medications you use, whether prescribed or self-selected?

Consider writing down your questions now to be prepared for the next time you visit your physician. Your doctor should evaluate all the medicine you take, even those non-prescription. Drugs don’t know the difference.

Exploring the HEART of Health

Thank you for reading this post. I strive to make them worth your time.

I share information and inspiration that sparks transformation in your body, mind, and spirit.

You can follow this blog in two easy ways. One is to put your email address into the box below.

Another way is to follow me on Facebook, where I share new posts, timely topics, photos, and an occasional cartoon.

Watercress Words by Dr. Aletha

Dr. Aletha

AI in Healthcare: Does It Enhance Patient Understanding?

Although many patients find AI helpful for understanding medical information, experts caution about potential inaccuracies and privacy risks, urging careful use and verification of AI-generated responses.

This information is current as of the date of original publication or update but may have changed by the time you read this. Do not use this information for diagnosis or treatment purposes. Before making health decisions, discuss with a qualified healthcare professional.

I recently had a medical procedure, and when the results came in via my patient portal, I logged in to read them. The diagnosis was something I don’t have much professional experience with, so I did what many patients do with their medical information. I went online and searched for information.

This time, I didn’t stop with a search engine. I used an AI assistant and was amazed at how easy it was not only to read information but also to ask questions and receive an answer. It even suggested additional resources and next steps.

Then I found this article on KFF indicating that I am not alone. And probably many of you have already used AI for this and other purposes. So I am sharing it here.

An AI Assistant Can Interpret Those Lab Results for You

(Edited for readability and length.)

written by Kate Ruder, September 15, 2025

When Judith Miller had routine blood work done in July, she got a phone alert the same day that her lab results were posted online. So, when her doctor messaged her the next day that her overall tests were fine, Miller wrote back to ask about the elevated carbon dioxide and low anion gap listed in the report.

While the 76-year-old Milwaukee resident waited to hear back, Miller did something patients increasingly do when they can’t reach their health care team. She put her test results into Claude and asked the AI assistant to evaluate the data.

Medical Records plus AI equals Understanding

“Claude helped give me a clear understanding of the abnormalities,” Miller said. The generative AI model didn’t report anything alarming, so she wasn’t anxious while waiting to hear back from her doctor, she said.

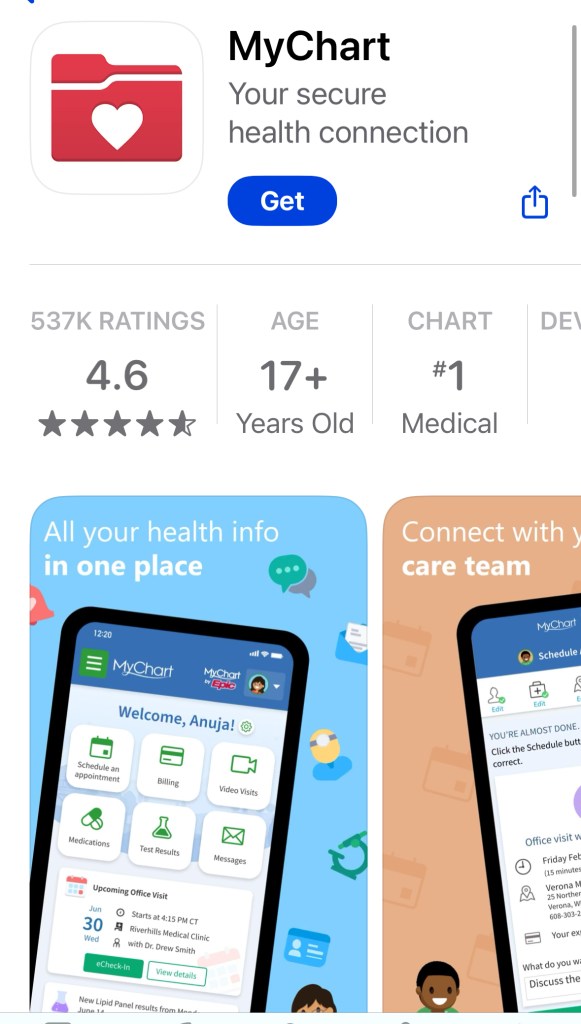
Patients have unprecedented access to their medical records, often through online patient portals such as MyChart. Federal law requires health organizations to immediately release electronic health information, such as notes on doctor visits and test results.

Screenshot of the MyChart app

A study published in 2023 found that 96% of patients surveyed want immediate access to their records, even if their provider hasn’t reviewed them.

And many patients are using large language models, or LLMs, like OpenAI’s ChatGPT, Anthropic’s Claude, and Google’s Gemini, to interpret their records.

Use AI for Health Cautiously

That help comes with some risk, though. Physicians and patient advocates warn that AI chatbots can produce wrong answers and that sensitive medical information might not remain private.

Yet, most adults are cautious about AI and health. Fifty-six percent of those who use or interact with AI are not confident that information provided by AI chatbots is accurate, according to a 2024 KFF poll. (KFF is a health information nonprofit that includes KFF Health News.)

“LLMs are theoretically very powerful and they can give great advice, but they can also give truly terrible advice depending on how they’re prompted,”

Adam Rodman, internist at Beth Israel Deaconess Medical Center

Adam Rodman Is an internist at Beth Israel Deaconess Medical Center in Massachusetts and the chair of a steering group on generative AI at Harvard Medical School.

Justin Honce, a neuroradiologist at UCHealth in Colorado, said it can be very difficult for patients who are not medically trained to know whether AI chatbots make mistakes.

“Ultimately, it’s just the need for caution overall with LLMs. With the latest models, these concerns are continuing to get less and less of an issue but have not been entirely resolved,” Honce said.

Rodman has seen a surge in AI use among his patients in the past six months. In one case, a patient took a screenshot of his hospital lab results on MyChart then uploaded them to ChatGPT to prepare questions ahead of his appointment.

Rodman said he welcomes patients’ showing him how they use AI, and that their research creates an opportunity for discussion.

Roughly 1 in 7 adults over 50 use AI to receive health information, according to a recent poll from the University of Michigan, while 1 in 4 adults under age 30 do so, according to the KFF poll.

Photo by Beyzaa Yurtkuran on Pexels.com

Should AI Give Medical Advice?

Using the internet to advocate for better care for oneself isn’t new. Patients have traditionally used websites such as WebMD, PubMed, or Google to search for the latest research and have sought advice from other patients on social media platforms like Facebook or Reddit.

But AI chatbots’ ability to generate personalized recommendations or second opinions in seconds is novel.

Liz Salmi, communications and patient initiatives director at OpenNotes, an academic lab at Beth Israel Deaconess that advocates for transparency in health care, had wondered how good AI is at interpretation, specifically for patients.

In a proof-of-concept study published this year, Salmi and colleagues analyzed the accuracy of ChatGPT, Claude, and Gemini responses to patients’ questions about a clinical note. All three AI models performed well, but how patients framed their questions mattered, Salmi said

For example, telling the AI chatbot to take on the persona of a clinician and asking it one question at a time improved the accuracy of its responses.

Are Medical Records Private with AI?

Privacy is a concern, Salmi said, so it’s critical to remove personal information like your name or Social Security number from prompts. Data goes directly to tech companies that have developed AI models, Rodman said, adding that he is not aware of any that comply with federal privacy law or consider patient safety

Sam Altman, CEO of OpenAI, warned on a podcast last month about putting personal information into ChatGPT.

“Many people who are new to using large language models might not know about hallucinations,” Salmi said, referring to a response that may appear sensible but is inaccurate.

For example, OpenAI’s Whisper, an AI-assisted transcription tool used in hospitals, introduced an imaginary medical treatment into a transcript, according to a report by The Associated Press.

Using generative AI demands a new type of digital health literacy that includes asking questions in a particular way, verifying responses with other AI models, talking to your health care team, and protecting your privacy online, said Salmi and Dave deBronkart, a cancer survivor and patient advocate who writes a blog devoted to patients’ use of AI.

Photo by Anna Shvets on Pexels.com

Can AI help physicians communicate results?

Patients aren’t the only ones using AI to explain test results. Stanford Health Care has launched an AI assistant that helps its physicians draft interpretations of clinical tests and lab results to send to patients.

Colorado researchers studied the accuracy of ChatGPT-generated summaries of 30 radiology reports, along with four patients’ satisfaction with them. Of the 118 valid responses from patients, 108 indicated the ChatGPT summaries clarified details about the original report.

But ChatGPT sometimes overemphasized or underemphasized findings, and a small but significant number of responses indicated patients were more confused after reading the summaries, said Honce, who participated in the preprint study.

Meanwhile, after four weeks and a couple of follow-up messages from Miller in MyChart, Miller’s doctor ordered a repeat of her blood work and an additional test that Miller suggested. The results came back normal.

Miller was relieved and said she was better informed because of her AI inquiries.

“It’s a very important tool in that regard,” Miller said. “It helps me organize my questions and do my research and level the playing field.”

KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.

Subscribe to KFF Health News’ free Morning Briefing.

This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NoDerivatives 4.0 International License.

This article also appeared on NPR.ORG.

AI in Medical Education

I graduated from college, medical school, and residency without using a computer for training or patient care. When computers and the internet came into widespread use, medical education and medical practice changed to embrace that new technology.

Now AI is doing the same thing. Here you can learn how Harvard Medical School is building artificial intelligence into the curriculum to train the next generation of doctors.

Reflection and Response

I hope you have learned something new in this post, or it confirms something you already knew.

How are you using technology to manage your healthcare? Do you use options such as

  • health record portals
  • online scheduling
  • video visits
  • internet search for medical information, with or without AI

Were you aware that doctors are using AI to create office notes and result summaries?

What concerns do you have about the value and safety of using AI in healthcare? What else do you need to know or want to learn about AI use ?

Cover Image

The cover image was created by the Jetpack AI Assistant from Automatic, Inc.

Exploring the HEART of Health

I hope the information in this post gives you inspiration.

Thank you for reading this post. I strive to make them worth your time.

I share information and inspiration that sparks transformation in your body, mind, and spirit.

You can follow this blog in two easy ways. One is to put your email address into the box below.

Another way is to follow me on Facebook, where I share new posts, timely topics, photos, and an occasional cartoon.

Watercress Words by Dr. Aletha

Medical stethoscope and heart on a textured background

Dr Aletha